
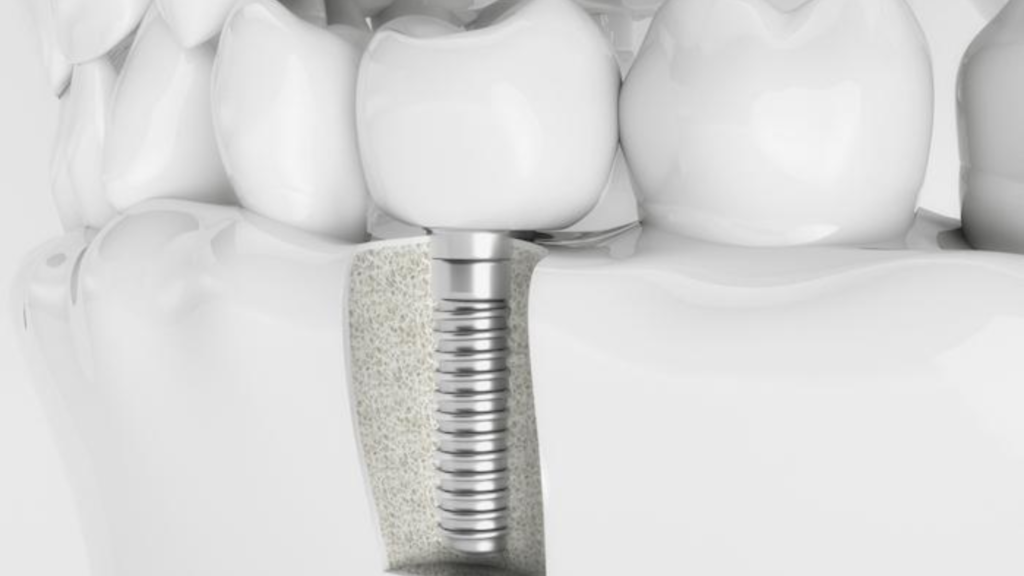
You’re thinking about dental implants. Maybe your dentist mentioned them, maybe a friend had them done, or maybe you’ve been Googling at 2 AM because your dentures slipped during dinner again.
The natural next question: am I actually a candidate?
The honest answer: most adults with missing teeth are. But “most” isn’t “all,” and the internet is full of both false reassurances and unnecessary scare stories. This guide walks through the real signs that you’re likely a good candidate, the conditions that don’t disqualify you (even though you may have heard otherwise), and the situations where implants genuinely aren’t the right choice.
Written by Dr. Rushabh Doshi at SmileOn Dental Implants, who has evaluated thousands of candidacy cases and routinely tells patients both “yes, you’re a candidate” and “not for you – here’s what I’d recommend instead.”
8 signs you’re likely a good candidate
These aren’t guarantees – only a 3D scan can confirm candidacy – but if several of these describe you, you’re probably in the 90%+ of patients who qualify.
1. You’re missing one or more teeth
This is the baseline. Dental implants replace missing teeth – whether you’ve lost one tooth to decay, several to gum disease, or an entire arch to years of dental problems. The number of missing teeth doesn’t determine whether you’re a candidate; it determines which type of implant treatment fits.
2. Your overall health is reasonably good
Dental implant surgery is a minor outpatient procedure – comparable to a tooth extraction in terms of physical demand. If you’re healthy enough for a tooth extraction, you’re almost certainly healthy enough for an implant.
“Reasonably good health” doesn’t mean perfect health. It means your chronic conditions (if any) are managed and stable. Controlled diabetes, treated high blood pressure, managed heart conditions, well-monitored osteoporosis – all compatible with implant surgery.
3. Your gums are healthy (or treatable)
Healthy gums are important because the tissue around the implant needs to heal properly and maintain a seal against bacteria long-term. If you have active gum disease right now, that doesn’t disqualify you – it means the gum disease needs to be treated first.
Most gum disease is treatable with deep cleaning (scaling and root planing), improved home care, and sometimes antibiotics. Once treated, the vast majority of patients become implant candidates.
4. You have adequate jawbone (or it can be restored)
The implant needs to be anchored in bone. Adequate bone means enough width, height, and density at the planned implant site to house the fixture with a margin of safety around it.
Here’s the key point: “not enough bone” is rarely a permanent disqualifier. Bone grafting can restore lost volume in most patients. The All-on-X technique uses angled implants to engage bone that other approaches can’t reach. Zygomatic implants anchor into the cheekbone for patients with severe upper-jaw loss.
About 90% of patients who’ve been told they lack sufficient bone turn out to be candidates when evaluated with modern techniques. Full bone loss guide →
5. Your jaw is fully grown
Implants are placed in mature bone that has finished growing. This means:
- Women: typically age 16–18+
- Men: typically age 18–21+
- Adults of any age beyond this: no upper limit
If you’re an adult, you meet this criterion.
6. You don’t smoke – or you’re willing to quit during healing
Non-smokers are ideal implant candidates. Smokers can receive implants but face 2–3× higher failure rates during the first year. Quitting 2+ weeks before surgery and remaining smoke-free for 3 months after dramatically improves outcomes.
If you’re a smoker who’s willing to quit temporarily for the healing period, you’re still a candidate. If you’re a heavy smoker who won’t stop under any circumstances, the risk-benefit conversation changes – but doesn’t necessarily rule implants out.
7. You’re committed to basic oral hygiene
Implants don’t get cavities, but they can fail from neglect. Patients who brush twice daily, floss (or use a water flosser), and keep their 6-month professional cleanings have implant success rates above 95% at 20 years.
You don’t need to be a hygiene perfectionist. You need to be consistent. If you brush daily and see a dentist regularly, you meet this criterion.
8. You have realistic expectations about the timeline
Dental implants are not instant (except for same-day All-on-X, which delivers temporary teeth in one day). A single implant takes 3–6 months from placement to final crown. If you’re looking for a solution measured in weeks, a bridge or temporary denture may serve as a bridge (literally) while the implant heals.
Patients who understand and accept the 3–6 month timeline tend to be the most satisfied with their outcomes.
5 conditions that don’t disqualify you (even though you may have heard otherwise)
“I have diabetes”
You’re likely still a candidate. Controlled diabetes (A1c under 7) has minimal impact on implant success rates. Even moderately controlled diabetes (A1c 7–8) can be compatible with implants, though healing may be slightly slower. Dr. Doshi coordinates with your physician when needed.
The disqualifying scenario: uncontrolled diabetes with A1c consistently above 8–9 and no plan to stabilize it. In that case, implant healing becomes unreliable.
“I have osteoporosis”
You’re likely still a candidate. Osteoporosis affects bone density systemically, but the jaw often retains adequate density for implants even when other bones are affected. Patients taking oral bisphosphonates (Fosamax, Actonel, Boniva) can generally proceed safely.
The caution: patients on IV bisphosphonates (Zometa, Reclast) – used for cancer-related bone conditions – require careful evaluation. IV bisphosphonates can affect jaw bone healing and increase risk of a rare complication called MRONJ (medication-related osteonecrosis of the jaw). Dr. Doshi coordinates with your oncologist or prescribing physician in these cases.
“I’m over 70 (or 80)”
Age is not a disqualifier. Dr. Doshi has successfully placed implants in patients through their mid-80s. What matters is overall health status, healing capacity, and the ability to undergo a 1–2 hour outpatient procedure. Many patients in their 70s and 80s are excellent candidates.
The question to ask isn’t “am I too old?” but rather “is my health sufficient for minor surgery and do I have enough years ahead to benefit from the investment?”
“I was told I don’t have enough bone”
You may still be a candidate – get a second opinion. The techniques available in 2026 are dramatically more advanced than what was available even 10 years ago. Bone grafting, sinus lifts, angled implants, short implants, and zygomatic implants have expanded candidacy to cover approximately 90% of patients previously rejected. A 3D CT scan – not a 2D X-ray – is the proper way to assess bone. Full guide →
“I wear dentures”
Current denture wearers are among the most common implant candidates. Whether you’ve worn dentures for 2 years or 20, there are options:
- All-on-X: permanently fixed teeth replacing your denture entirely ($24,000/arch)
- Implant-supported denture: your denture (or a new one) snaps onto 4 implants for dramatically better stability ($9,000/arch)
- Individual implants: if you’re only missing a few teeth and currently wear a partial denture, individual implants may be the right fit
Even long-term denture wearers with significant bone loss usually qualify for at least one of these options.
When you might NOT be a candidate
Transparency matters. Here are the situations where Dr. Doshi will likely recommend against implants or suggest alternative approaches:
Uncontrolled diabetes
An A1c consistently above 8–9 with no management plan compromises bone healing to the point where implant success becomes unreliable. The recommendation: work with your physician to stabilize blood sugar, then revisit implants when your A1c is in the 6.5–7.5 range.
Active cancer treatment
Chemotherapy and radiation therapy (especially radiation to the head and neck) suppress the immune system and impair bone healing. Implants are generally deferred until treatment is complete and the immune system has recovered. For patients who’ve finished cancer treatment 6+ months ago, implant candidacy is usually re-established.
Active, untreated gum disease
Placing an implant into infected tissue is a recipe for failure. Active periodontal disease must be resolved before implant surgery. This isn’t a permanent disqualification – it’s a sequence issue. Treat the gum disease first, then proceed with implants.
Severe, unaddressed grinding with no willingness to manage it
Extreme bruxism subjects implants to 3–5× normal forces. Patients willing to wear a nightguard can proceed safely. Patients who grind severely and refuse any protective measures face elevated long-term risk.
Certain medications
IV bisphosphonates (Zometa, Reclast) require careful evaluation. High-dose immunosuppressants (transplant patients) may affect healing. Anticoagulants can usually be managed but require coordination with your prescribing physician.
Insufficient bone with no graft option
This is genuinely rare in 2026. Most bone deficiencies can be addressed with grafting, sinus lifts, or alternative implant approaches. But in a small percentage of patients – typically those with extreme resorption after decades of denture wear combined with medical conditions that prevent grafting – the bone simply can’t support any implant configuration safely.
Very short remaining health horizon combined with tight budget
A patient in their late 80s or 90s with significant health challenges and a 2–3 year horizon may not benefit from the investment. In these cases, a well-made denture or implant-supported denture delivers most of the functional benefit at lower cost and complexity.
The self-assessment checklist
Before your consultation, run through these questions. The more “yes” answers, the more likely you’re a candidate:
- I have one or more missing teeth (or teeth that need extraction)
- My overall health is stable (any chronic conditions are managed)
- I don’t have untreated gum disease (or I’m willing to treat it first)
- I’m a non-smoker, or I’m willing to quit temporarily for healing
- I brush my teeth daily
- I’m over 18
- I’m willing to follow post-procedure instructions
- I’m prepared for a 3–6 month process (for single implants) or a same-day procedure (for All-on-X)
- I can budget for the investment (cash, financing, or a combination)
If you answered “yes” to 7 or more of these, you’re very likely a candidate. The consultation confirms it definitively.
What the consultation actually determines
No self-assessment replaces a clinical evaluation. The consultation at SmileOn includes:
- 3D cone-beam CT scan – measures bone volume, density, and location of nerves and sinuses with millimeter precision. This is the single most important diagnostic tool. It takes 15 seconds and is painless.
- Clinical exam – Dr. Doshi examines your gums, remaining teeth, bite, and jaw movement. He assesses gum health, identifies any conditions that need treatment first, and evaluates the overall complexity of your case.
- Medical history review – medications, chronic conditions, surgical history, and anything that could affect healing.
- Specific recommendation – based on the above, Dr. Doshi tells you:
- Whether you’re a candidate (and for which type of implant treatment)
- Whether any preparatory work is needed first (gum treatment, grafting)
- What the timeline and cost look like for your specific case
- Or, honestly, whether implants aren’t the right option and what he’d recommend instead
- Itemized cost quote and financing pre-qualification – so you leave knowing both the clinical answer and the financial answer.
The consultation takes 45–60 minutes and is complimentary for new patients at SmileOn. No obligation to proceed.
Frequently asked questions
Can I be a candidate if I only have one missing tooth?
Yes – single-tooth replacement is the most common type of dental implant procedure. One implant, one crown, one gap filled.
Can I be a candidate if I’m missing all my teeth?
Yes – this is what All-on-X is designed for. Four implants per arch replace a full set of teeth with a permanently fixed bridge. About 90% of patients with full tooth loss qualify. All-on-X guide →
What if my dentist said I’m not a candidate but I’m not sure?
Get a second opinion from an implant specialist. A general dentist evaluating candidacy with a 2D X-ray may reach a different conclusion than a fellowship-trained implantologist evaluating the same patient with a 3D CT scan and access to grafting, angled-implant, and zygomatic techniques. The second opinion is free at SmileOn.
Does being overweight affect candidacy?
Not directly. BMI is not a disqualifier for dental implant surgery. What matters is whether weight-related health conditions (diabetes, cardiovascular issues) are managed and stable.
Can I get implants while pregnant?
Elective surgery is generally deferred during pregnancy as a precaution. Implant placement is typically scheduled after delivery and after any breastfeeding period if the patient prefers to wait. The timing is a preference, not a permanent disqualification.
How do I know if I have enough bone without a scan?
You can’t. Bone volume under the gums isn’t visible or palpable. 2D X-rays show some information but miss bone width entirely. A 3D CT scan is the only reliable diagnostic tool. This is why the scan is included in every SmileOn consultation – it’s the diagnostic step that answers the candidacy question definitively.
Find out for sure
The self-assessment above gives you a reasonable estimate. The consultation gives you a definitive answer – based on your actual bone, your actual health, and your actual case.
Dr. Doshi has evaluated thousands of candidacy cases and will give you a straight answer: yes, not yet (here’s what needs to happen first), or no (here’s what I’d recommend instead).
Call (682) 563-5663 or schedule online.
Available at three DFW locations: Mansfield (360 Dental Lounge), Arlington (Arlington Dental Lounge), and Irving (Irving Family Dental).
Consultation is complimentary for new patients. Treatment plan recommendations require diagnostic evaluation, including imaging. Not applicable to patients with active untreated periodontal disease. Cannot be combined with insurance. Subject to clinical eligibility.